The Claims Payment That Took Seven Months Because a Reinsurer Audited the MRI Codes

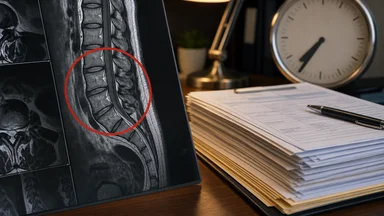
In the spring of 2025, a policyholder in the individual health market underwent an MRI of the lumbar spine. The procedure cost $47,000. The primary carrier approved the claim within 14 days. But the payment did not arrive. It took 210 days—seven months—for the check to clear. The reason: a reinsurer decided to audit the MRI codes.
A $47,000 claim approved in 14 days took seven months to pay. The delay had little to do with fraud or abuse. It originated in the reinsurer's audit of the ICD-10 code used for the MRI. The primary carrier had coded the claim as M54.5 (low back pain) with CPT 72148 (MRI lumbar spine without contrast). The reinsurer questioned whether the correct code was M54.1 (radiculopathy) with a cervical spine MRI code. That one-digit difference triggered a 90-day file review, followed by 60 days of arbitration, before the reinsurer finally reimbursed its share of $8,800. The policyholder waited 210 days for the full $47,000 payment.
The MRI That Went to Arbitration
The claim was straightforward on its face. A 55-year-old patient with documented lower back pain and radiculopathy received an MRI of the lumbar spine. The primary carrier's adjuster reviewed the clinical notes, confirmed medical necessity, and approved the $47,000 payment within two weeks. The claim was coded as ICD-10 M54.5 (low back pain) with CPT 72148 (MRI lumbar spine without contrast).
But the reinsurer—a major treaty partner that ceded roughly 40% of the carrier's individual book—flagged the claim for audit. Their medical director questioned whether the lumbar spine code was appropriate, suggesting the imaging might have been for the cervical spine (CPT 72141). The distinction mattered: cervical MRIs are less common for radiculopathy, and the reinsurer's internal guidelines required prior authorization for certain cervical codes. The coding mismatch, they argued, could indicate a documentation gap or, at worst, an upcoding attempt.
The primary carrier's adjuster defended the original code, providing additional clinical notes and a radiologist's report. The reinsurer was not satisfied. They demanded a full-file review, including all imaging orders, referrals, and prior authorization records. The carrier complied, but the review took 90 days. By then, the claim had aged past the carrier's normal payment cycle.
The dispute escalated to informal arbitration. Both sides appointed medical directors to review the case. The arbitrators eventually ruled in favor of the primary carrier, confirming the lumbar spine code was correct. But the arbitration process took another 60 days. Total elapsed time from claim submission to payment: 210 days. The cost of the audit—including medical director time, legal fees, and administrative overhead—exceeded $12,000, roughly a quarter of the claim amount.
Follow the Money: From Premium to Reinsurance Recovery
To understand why a reinsurer cares about a single $47,000 claim, you have to follow the money. The policyholder paid roughly $600 per month in premiums. Over a year, that is $7,200. The primary carrier, under its treaty reinsurance agreement, ceded 40% of the premium—about $2,880—to the reinsurer. In return, the reinsurer agreed to cover 40% of claims above a retention threshold, typically around $25,000 per claim.
For the $47,000 MRI claim, the carrier's retention was $25,000, meaning the reinsurer owed 40% of the remaining $22,000, or $8,800. But the reinsurer's obligation was contingent on the claim being valid under the treaty terms. The audit clause gave the reinsurer the right to review any claim for coding accuracy, medical necessity, and documentation completeness. If they found a material error, they could deny recovery entirely, leaving the carrier to pay the full $47,000 out of its own capital.
The carrier's loss ratio—the percentage of premiums paid out as claims—depends on timely reinsurance recoveries. If the $8,800 recovery is delayed by seven months, the carrier's incurred-but-not-paid claims swell, inflating the loss ratio for that quarter. For a small carrier with a block of 10,000 policies, a handful of delayed recoveries can shift the loss ratio by a percentage point or more. Regulators and rating agencies watch loss ratios closely; a sudden spike can trigger additional reserve requirements or a downgrade.
As a single fleet insurer's MGA arrangement shows, the cession structure matters. In that case, the managing general agent ceded two-thirds of premium before the first policy year. Here, the cession is smaller, but the audit risk is real. The reinsurer's right to audit is a lever that can freeze cash flow for months.
The Code Audit: A $47,000 Claim Hangs on a Digit
The audit focused on a single digit in the ICD-10 code. The primary carrier used M54.5 (low back pain). The reinsurer's medical director argued that the clinical notes supported a diagnosis of cervical radiculopathy, which would be coded as M54.1 (radiculopathy) with a cervical spine MRI code. The difference is one digit: M54.5 vs. M54.1. But that digit determines whether the imaging is lumbar or cervical, and whether the reinsurer's prior authorization rules apply.
The reinsurer's guidelines required prior authorization for cervical spine MRIs because of higher costs and lower frequency. The carrier had not obtained prior authorization because they coded it as lumbar. The reinsurer saw this as a potential control failure. If the carrier routinely coded cervical MRIs as lumbar to bypass authorization, the reinsurer's loss experience would deteriorate. The audit was not just about this claim; it was about pattern detection.
The primary carrier's adjuster pushed back, citing the radiologist's report that explicitly stated "lumbar spine" and the patient's history of lumbar disc disease. The reinsurer's medical director remained unconvinced, requesting the original imaging order from the referring physician. That order, when produced, confirmed the lumbar spine. But by then, the audit had consumed 90 days.
The cost of the audit—roughly $12,000 in internal and external expenses—exceeded the reinsurer's exposure on the claim ($8,800). From a pure financial standpoint, the audit was a losing proposition. But reinsurers do not audit claims individually; they audit to enforce underwriting discipline across the entire book. A single successful audit can deter hundreds of future coding errors, saving far more than the cost of one review.
Who Decides When the Reinsurer Says No?
The treaty language gave the reinsurer broad audit rights. Typically, these clauses allow the reinsurer to inspect the carrier's claims files, medical records, and billing documentation at any time. The treaty does not specify a timeline for the audit or for resolving disputes. The carrier is contractually obligated to cooperate, but there is no penalty for the reinsurer's delay.
When the reinsurer says no—or merely questions a claim—the carrier faces a choice. It can advance the payment from its own capital, hoping to recover later. Or it can wait for the audit to conclude, leaving the policyholder unpaid. Most carriers choose to wait, especially on large claims, because advancing payment ties up capital that could be used for other claims or investments. The policyholder bears the time cost: delayed medical care, collection threats from the hospital, and frustration.
In this case, the carrier advanced the $47,000 after 60 days, when it became clear the audit would take months. The advance came from the carrier's working capital, reducing its liquidity. The reinsurer reimbursed the $8,800 only after the arbitration ruling, seven months later. During those months, the carrier's balance sheet showed a $47,000 claim paid but only $8,800 recoverable, creating a temporary hole in its reserves.
The asymmetry of power is stark. The reinsurer can delay without consequence. The carrier must pay or risk regulatory action. The policyholder has no contractual relationship with the reinsurer and no recourse. As one insurtech's use of real-time braking data shows, innovation often focuses on pricing and underwriting, not on the claims back-end. The audit process remains a black box.
The Arithmetic of Delay: Loss Ratios and Reserve Strain
The delay's impact on the carrier's financials is measurable. The carrier holds the $47,000 as an incurred-but-not-paid claim during the audit period. Statutory accounting requires the carrier to establish a reserve for the full amount, even if reinsurance is expected. The reserve reduces the carrier's surplus—its capital cushion against unexpected losses.
If the carrier's loss ratio is calculated quarterly, the $47,000 claim appears in the numerator (incurred losses) but the $8,800 reinsurance recovery does not appear until the dispute is resolved. For a carrier with $10 million in quarterly premiums, a single $47,000 claim represents 0.47% of premium. A handful of such claims can shift the loss ratio by a full percentage point. Regulators may flag the carrier for "adverse loss development" and require additional reserves, further straining surplus.
The reinsurance recoverable—the $8,800—ages as an asset on the balance sheet. If it remains unpaid for more than 90 days, it is considered "aged" and may be discounted or written down. Rating agencies view large aged recoverables as a sign of weak reinsurance credit or poor claims management. The carrier's credit rating could be affected, raising its cost of capital.
For small to mid-size carriers, the cumulative effect of multiple delayed recoveries can be severe. A 2024 survey by Deloitte found that roughly 15% of health insurance claims subject to reinsurance audit faced delays exceeding 60 days. The average delay was 45 days, but the tail was long: some claims took over a year. The carriers with the thinnest capital margins were the most vulnerable.
What the Seven Months Reveal About Health Insurance Design
The seven-month delay is not an anomaly; it is a feature of the current system. Reinsurers have legitimate concerns about fraud, coding errors, and medical necessity. But the audit process is designed for their convenience, not for speed. The carrier, caught between the policyholder and the reinsurer, has little leverage.
Policy language rarely addresses audit timelines. Most health insurance policies state that claims will be paid within 30 to 45 days of receipt, but they carve out exceptions for "reasonable investigation." That exception swallows the rule. The policyholder has no contractual right to a quick audit. The carrier cannot compel the reinsurer to act faster.
Transparency initiatives, like the one auto telematics leakage map that showed premium drift, focus on the front end—pricing, underwriting, and coverage explanations. The claims back end remains opaque. Farmers Insurance recently launched an effort to make insurance easier to understand, but it focused on coverage options, not on claims audit procedures. The seven-month MRI claim would not be captured by such initiatives.
Coding complexity rewards large carriers with dedicated coding teams and legal resources. Smaller carriers and startups, which often rely on third-party administrators, are more vulnerable to audit delays. The asymmetry is structural. Until audit timelines are standardized and enforced, the policyholder will continue to pay the price—not in dollars, but in time.
Practical Takeaways for Carriers and Reinsurers
There are steps that carriers and reinsurers can take to reduce the friction. First, treaty language should include hard deadlines for audit resolution. For example, the reinsurer could be required to complete its initial review within 30 days and escalate disputes to arbitration within 60 days. If the deadline is missed, the reinsurer forfeits its right to deny recovery. Some European reinsurers have adopted such clauses; U.S. market practice has been slower to change.
Second, parametric triggers could be used for low-value disputes. If the claim amount is below a threshold—say, $50,000—and the audit cost exceeds the potential recovery, the reinsurer could automatically accept the claim. The cost savings would offset the occasional erroneous payment. This is similar to the approach used by African Risk Capacity, which uses parametric triggers for drought insurance, as described in a 2023 report by the World Bank's Global Facility for Disaster Reduction and Recovery.
Third, carriers should standardize code-review protocols upfront. Pre-audit checklists, agreed upon by both parties, can reduce the back-and-forth. If the carrier submits a complete file with supporting documentation, the reinsurer's audit should be limited to a checklist review, not a full-file reexamination. This would cut the average audit time from 90 days to perhaps 30 days.
Finally, policyholders should be informed of audit risk in the policy summary. A simple disclosure—"Large claims may be subject to reinsurer audit, which can delay payment by up to 90 days"—would set expectations. It would also create pressure on carriers and reinsurers to improve timelines, because informed consumers might choose plans with faster claims processes.
None of these changes require a wholesale redesign of the reinsurance market. They require only that both parties acknowledge that time has a cost. The seven-month MRI claim is a reminder that the insurance system's hidden gears can grind slowly. With better design, they can grind faster.